ASD Device Closure vs Open Heart Surgery

ASD Device Closure vs Open Heart Surgery

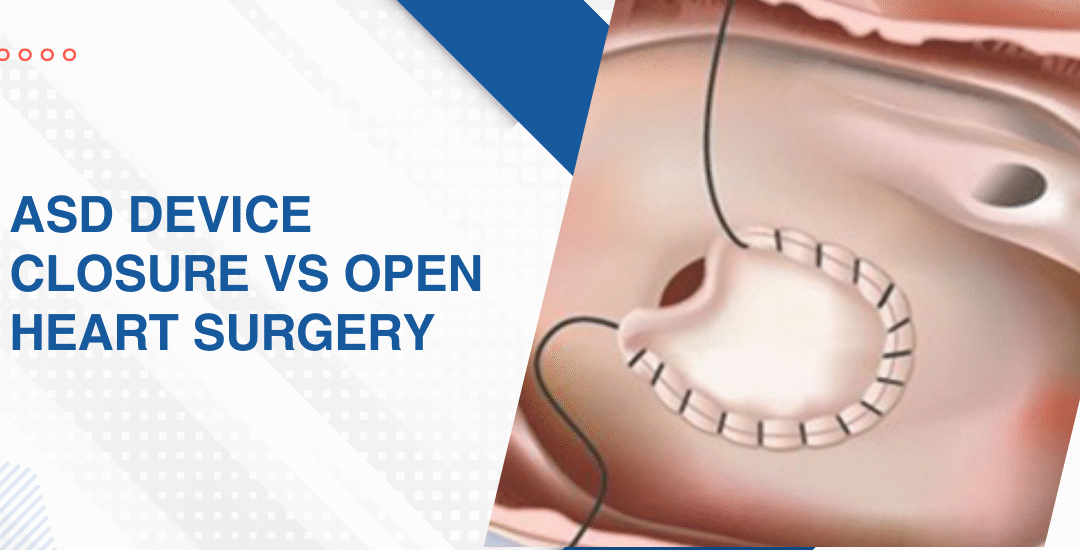
Neither is universally better. Device closure is less invasive, faster recovery, no chest opening, but it only works for specific ASD types and sizes where the anatomy actually supports a device sitting securely inside the defect. Open heart surgery works for virtually every ASD but carries a longer recovery and the risks that come with any procedure on cardiopulmonary bypass. The anatomy decides. Not the preference.

“Parents come in wanting to know which option is better and I always tell them the same thing. The better option is the one your child’s anatomy makes possible and safe. Starting from a preference and working backwards to the anatomy is the wrong way around completely,“ says Dr. Prashant Bobhate, Pediatric Cardiologist in Mumbai, India

What Makes Device Closure the Right Choice for Some ASDs?

Device closure works when the anatomy genuinely supports it and in those cases it’s a genuinely attractive option because it avoids open heart surgery entirely while achieving the same haemodynamic result if the defect sits in the right location with enough tissue rim around it.

  • Secundum ASDs: The most common ASD type and the one most suitable for device closure because it sits in the middle of the atrial septum where catheter access is straightforward and where the tissue rim around the defect is usually adequate to anchor a device securely.
  • Size matters: Defects up to around 38 to 40mm can potentially be closed by device but the ratio of defect size to total septal length matters as much as the raw measurement and that assessment only comes from a detailed echo in experienced hands.
  • Rim adequacy: A defect with poor rim tissue near the aorta or the pulmonary veins can’t hold a device properly regardless of its size and deploying one anyway is how complications happen that a straightforward surgical repair would have avoided.
  • Recovery difference: A child who has device closure goes home in one to two days, returns to normal activity within a week and carries no chest scar while a surgical repair means a week in hospital, six weeks of activity restriction and a sternotomy scar that lasts forever.

If your child has been told they have an ASD and needs assessment for the right closure approach, understanding what that decision involves starts with a proper atrial septal defect evaluation that maps the anatomy before anyone discusses options

When Does Open Heart Surgery Become the Only Answer?

When the anatomy rules device closure out. 

  • Sinus venosus ASDs: These sit near the entry of the pulmonary veins and no catheter device can close them safely or effectively which makes surgical repair the only appropriate option regardless of how much a family might prefer to avoid open heart surgery.
  • Large deficient rims: When the tissue border around the defect is too thin or absent in multiple directions a device has nothing solid to grip and the risk of embolisation or erosion into adjacent cardiac structures makes surgery the clearly safer path.
  • Associated anomalies: Some ASDs come with partial anomalous pulmonary venous drainage or other structural problems that need direct surgical correction at the same time and a catheter in the femoral vein simply can’t address everything that needs fixing in that situation.
  • Failed device attempt: Occasionally a device closure is attempted, the anatomy doesn’t cooperate and the procedure is abandoned in favour of surgery and a centre experienced in both approaches can pivot without the family losing time or the child losing ground.

Parents wanting to understand where unrepaired cardiac shunts eventually lead when they go unaddressed for too long should read this piece on when lung transplant becomes necessary for pulmonary hypertension because the pressure consequences of an untreated ASD don’t always wait as long as people assume.

Why Choose Dr. Prashant Bobhate for ASD Closure in Mumbai?

An ASD assessment isn’t just measuring the hole. It’s reading the rim tissue, assessing the relationship to the pulmonary veins, understanding what the right atrium has already absorbed and then giving a family a clear answer about which approach is actually on the table for their child and why. Not a default recommendation. A real anatomical decision. Dr. Prashant Bobhate has spent over 12 years performing interventional paediatric cardiology including catheter-based ASD closures and managing the surgical planning pathway for defects that need open repair at the Children’s Heart Centre, Kokilaben Dhirubhai Ambani Hospital.

Schedule a consultation to find out if a cure is possible and what the right treatment plan looks like for you.

FAQs

Is device closure safer than open heart surgery for ASD?

For suitable anatomy yes because it avoids cardiopulmonary bypass entirely but in anatomy that doesn’t support a device attempting catheter closure is riskier not safer than going straight to surgery.

At what age can ASD device closure be done?

Generally from around two years and above depending on body weight and defect size but timing depends on the haemodynamic impact the defect is having not on reaching a specific birthday.

Can an ASD close on its own without any procedure?

Small secundum ASDs in infants sometimes close spontaneously in the first two years of life but moderate and large defects rarely do and need either device closure or surgical repair before the right heart absorbs cumulative damage.


How long does ASD device closure take?

The procedure itself usually takes around 30 to 60 minutes under general anaesthesia and most children go home the following day with a follow-up echo scheduled at one month to confirm the device is sitting correctly.

References:

Can Down Syndrome Children Have Heart Defects?

Can Down Syndrome Children Have Heart Defects?

Yes and the number is higher than most families expect. Around 40 to 50 percent of children born with Down syndrome have a congenital heart defect and in many cases that defect is the most urgent medical issue in the first weeks of life, not the chromosomal diagnosis itself. Holes between chambers, malformed valves, abnormal connections these need a cardiac assessment from day one, not somewhere down the line when symptoms finally show up.

“When a Down syndrome baby is born I want an echo done before that family leaves the hospital. Not because something might be wrong. Because nearly half the time something is wrong and the families who find out late are the ones with the hardest conversations ahead,” says Dr. Prashant Bobhate, Pediatric Cardiologist in Mumbai, India.

What Heart Defects Are Common in Down Syndrome Children?

Not random. There’s a very specific pattern to the cardiac defects that show up in Down syndrome and knowing that pattern is what lets a specialist move fast rather than investigate from scratch.

  • AVSD: This one is almost diagnostic of Down syndrome on its own  a large hole spanning both the atrial and ventricular septa with a single malformed valve where two valves should normally exist, and it almost always needs surgery before six months.
  • VSD: These show up frequently in Down syndrome children and size is everything here because a small VSD might close on its own while a large one is already overloading the lungs from the first weeks of life.
  • ASD: Smaller atrial defects get dismissed more than they should and even the ones causing no immediate haemodynamic trouble need a proper echo follow-up plan rather than a handwave and a come-back-later.
  • TOF: A smaller proportion but it happens and a Down syndrome child with tetralogy of Fallot needs urgent specialist input because that combination doesn’t give you the luxury of watching and waiting.

Every Down syndrome child needs a full cardiac assessment from birth and congenital heart disease evaluation is what maps the anatomy, the pressures and the plan before time runs out on the safest window for correction.

When and How Are These Defects Treated?

Prevention first. Then damage control. Surgery only when the valve has gone too far.

  • Penicillin injections: Any child who has had confirmed rheumatic fever needs monthly benzathine penicillin for years, sometimes decades, to stop recurrent strep from adding more damage to what’s already there.
  • Echo surveillance: Regular echocardiography tracks how the valve is changing and catches the point where waiting becomes genuinely riskier than stepping in and doing something about it.
  • Symptom medications: Diuretics and vasodilators manage the haemodynamic load in symptomatic children who aren’t yet at the threshold where a procedure becomes the better option.
  • Balloon or surgery: When mitral stenosis is severe enough to impair output and daily life, balloon dilatation or surgical repair is the only real way to restore forward flow and give the left atrium some relief.

Parents wanting to understand what cardiac warning signs look like in children before any formal valve diagnosis gets made should read this piece on top 5 warning signs of pediatric heart failure because catching it early is always what keeps the most options open.

Why Choose Dr. Prashant Bobhate for Down Syndrome Heart Care in Mumbai?

Most families with a Down syndrome diagnosis are already managing more information than they expected in those first days. They don’t need vague optimism from a cardiologist who sees one AVSD a year. They need someone who can look at the echo, say plainly what’s there and tell them exactly what happens next and when. Dr. Prashant Bobhate has spent over 12 years managing congenital heart disease in Down syndrome children across every defect type, every complexity and every stage from neonatal diagnosis through surgical planning and long term follow up at the Children’s Heart Centre, Kokilaben Dhirubhai Ambani Hospital.

Schedule a consultation to find out if a cure is possible and what the right treatment plan looks like for you.

FAQs

Do all Down syndrome children have heart defects?

No but nearly half do and an echo at birth is non-negotiable for every single one of them regardless of what the clinical exam shows.

What is the most common heart defect in Down syndrome?

AVSD a large combined hole in both septa with a malformed valve and it needs surgical repair before six months in most cases

Can Down syndrome heart defects be safely operated on?

Yes and outcomes are good in experienced centres when the timing is right and lung pressures haven’t already climbed to where surgery becomes the riskier option.


What happens if the defect goes untreated?

Irreversible lung damage within the first year of life. Surgery becomes impossible and the child is left managing a condition that was entirely preventable if anyone had acted earlier.

References:

What Is Rheumatic Heart Disease And How Is It Caused n Children

What Is Rheumatic Heart Disease And How Is It Caused n Children

Rheumatic heart disease is permanent valve damage caused by rheumatic fever, itself triggered by an untreated group A streptococcal throat infection. The immune system meant to fight the bacteria turns on the heart valves instead and that misdirected attack leaves scar tissue that stiffens and narrows valves in ways the heart simply can’t recover from without intervention.

“The tragedy of rheumatic heart disease is that it’s almost entirely preventable and yet I still see children with severely damaged mitral valves from a strep throat written off as a viral fever three or four years earlier,” says Dr. Prashant Bobhate, Pediatric Cardiologist in Mumbai, India.

What Actually Causes Rheumatic Heart Disease in Children?

The bacteria infects the throat and if nobody treats it properly the immune response that follows doesn’t stay where it belongs.

  • Strep ignored: An untreated streptococcal throat infection triggers antibodies that cross-react with cardiac tissue because the bacterial proteins look enough like heart valve proteins to confuse the immune system completely.
  • Repeated infections: One episode damages the valve somewhat but each recurrent strep infection in a child without penicillin prophylaxis adds another layer of scarring that compounds quietly with every round.
  • Mitral valve: This is the valve that takes the worst hit and the leaflets gradually thicken, fuse at the tips and lose the flexibility they need to open and close across a lifetime of beats.
  • Poverty drives it: Overcrowded homes, no antibiotics nearby and delayed care all mean strep throat goes untreated long enough to start the whole cascade and India carries a disproportionately high burden of this disease for exactly that reason.

Children showing breathlessness, reduced stamina or a murmur after a history of recurrent throat infections need urgent specialist assessment and pediatric heart failure management starts with knowing exactly what the valves look like right now.

How Is Rheumatic Heart Disease Managed in Children?

Prevention first. Then damage control. Surgery only when the valve has gone too far.

  • Penicillin injections: Any child who has had confirmed rheumatic fever needs monthly benzathine penicillin for years, sometimes decades, to stop recurrent strep from adding more damage to what’s already there.
  • Echo surveillance: Regular echocardiography tracks how the valve is changing and catches the point where waiting becomes genuinely riskier than stepping in and doing something about it.
  • Symptom medications: Diuretics and vasodilators manage the haemodynamic load in symptomatic children who aren’t yet at the threshold where a procedure becomes the better option.
  • Balloon or surgery: When mitral stenosis is severe enough to impair output and daily life, balloon dilatation or surgical repair is the only real way to restore forward flow and give the left atrium some relief.

Parents wanting to understand what cardiac warning signs look like in children before any formal valve diagnosis gets made should read this piece on top 5 warning signs of pediatric heart failure because catching it early is always what keeps the most options open.

Why Choose Dr. Prashant Bobhate for Rheumatic Heart Disease Care in Mumbai?

You want someone who can look at the valve on echo, tell you honestly where it’s heading and have the real conversation about what twelve looks like now and what twenty-five looks like if nothing changes. Not a soft answer designed to make the appointment feel better. A plan. Dr. Prashant Bobhate has spent over 12 years managing paediatric valve disease from early subclinical rheumatic damage through severe mitral involvement requiring intervention at the Children’s Heart Centre, Kokilaben Dhirubhai Ambani Hospital.

Schedule a consultation to find out if a cure is possible and what the right treatment plan looks like for you.

FAQs

Can rheumatic heart disease be cured in children?

The damage already done can’t be undone but progression stops with consistent penicillin prophylaxis and severely damaged valves can be repaired or replaced when intervention becomes necessary.

How common is rheumatic heart disease in India?

Very common. Delayed antibiotic access, overcrowding and late diagnosis mean strep throat progresses to rheumatic fever here far more often than it should and India carries one of the highest RHD burdens globally.

What are the first signs of rheumatic heart disease in a child?

Breathlessness during activity, reduced stamina, joint pains after a recent throat infection or a newly detected murmur are the signs that should send a family straight to a paediatric cardiologist without waiting.

Does every child with rheumatic fever develop heart disease?

Not every child but around 30 to 45 percent with untreated rheumatic fever develop some valve damage which is exactly why penicillin prophylaxis after any confirmed episode isn’t optional.

References:

Is Hypertrophic Cardiomyopathy In Children Dangerous?

Is Hypertrophic Cardiomyopathy In Children Dangerous?

Yes. Hypertrophic cardiomyopathy is a leading cause of sudden cardiac death in young athletes and children, making it one of the most serious cardiac diagnoses a family can receive. But dangerous doesn’t mean hopeless. Most children with a confirmed HCM diagnosis can lead normal lives with proper treatment, careful monitoring and a management plan built around their specific risk profile by a paediatric cardiologist who actually understands the condition.

“HCM is one of those diagnoses that families come to me genuinely not knowing what to do with because the child looks well, plays normally and then you show them the echo and they can’t reconcile the two pictures at all,” says Dr. Prashant Bobhate, Pediatric Cardiologist in Mumbai, India.

What Makes HCM Dangerous in Children?

HCM thickens the heart muscle in ways that obstruct blood flow, destabilise the electrical system and in high-risk children create conditions for sudden cardiac death during activity nobody saw coming.

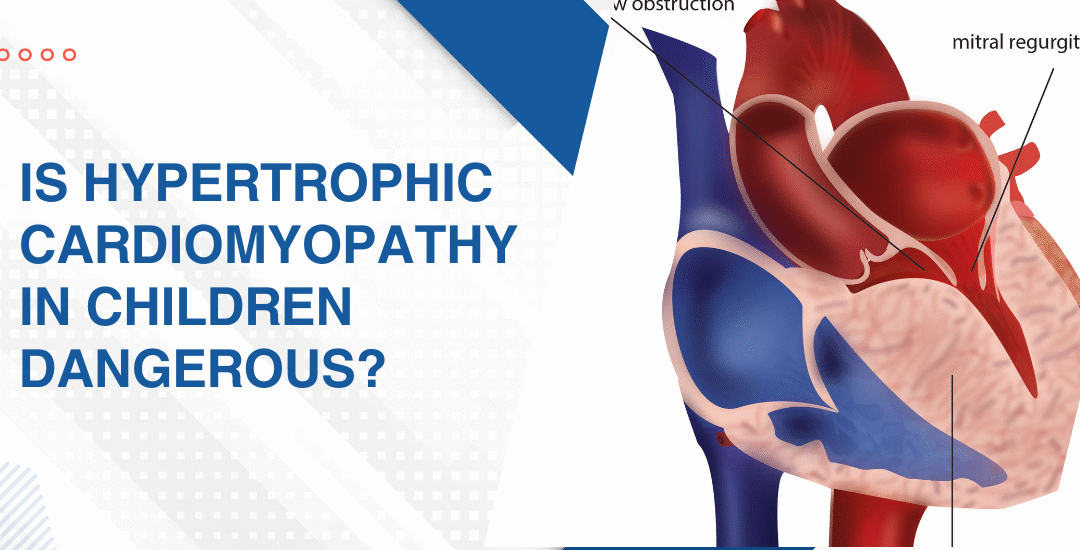
  • Outflow obstruction: The thickened septum partially blocks blood leaving the heart and that blockage worsens under exertion when the heart needs more output not less.
  • Dangerous arrhythmias: Disorganised muscle fibres create an unstable electrical substrate that can trigger ventricular fibrillation especially during physical stress in children with undiagnosed HCM.
  • Diastolic dysfunction: The stiff thickened ventricle doesn’t relax properly between beats so filling is impaired even when the pumping function looks normal on a basic assessment.
  • Mitral valve involvement: The abnormal septal bulge pulls the mitral leaflet into the outflow tract creating dynamic obstruction and mitral regurgitation simultaneously which significantly worsens the haemodynamic burden.

Every child with confirmed or suspected HCM needs a detailed structural assessment and 2D echocardiography for children maps the hypertrophy, outflow gradient and electrical risk before any management decision gets made.

How Is HCM Diagnosed and Managed in Children?

Diagnosis starts with an echo. Management depends entirely on severity.

  • Genetic testing: First-degree relatives of any diagnosed child have a 50% chance of carrying the same mutation so family screening with ECG and echo is standard care not optional.
  • Activity restrictions: High-intensity competitive sport in a child with significant outflow obstruction or arrhythmia risk is genuinely dangerous and restrictions must come from a specialist assessment not a general opinion.
  • Medications: Beta-blockers and calcium channel blockers reduce the outflow gradient and improve diastolic filling making a real difference to exercise tolerance when titrated properly.
  • ICD implantation: Children with prior cardiac arrest, sustained ventricular tachycardia or extreme hypertrophy on echo need an implantable defibrillator because medication alone doesn’t reliably prevent sudden death in high-risk cases.

Parents wanting to understand how early cardiac detection shapes HCM management should read this piece on whether a fetal echo can detect baby heart defects because identifying abnormalities early is always what expands the options available.

Why Choose Dr. Prashant Bobhate for HCM Care in Mumbai?

HCM in a child needs someone who can measure the outflow gradient under provocation, interpret Holter findings in the full clinical context and have the honest conversation about what sport means for that specific child’s risk profile. Not a generic restriction. A real assessment built around that one child. Dr. Prashant Bobhate has spent over 12 years managing complex paediatric cardiac conditions including hypertrophic cardiomyopathy, arrhythmia risk stratification and sudden cardiac death prevention across every age group at the Children’s Heart Centre, Kokilaben Dhirubhai Ambani Hospital.

Schedule a consultation to find out if a cure is possible and what the right treatment plan looks like for you.

FAQs

Can a child with HCM live a normal life?

Many can with proper monitoring and medication but the answer depends entirely on the degree of hypertrophy and individual arrhythmia risk assessed by a specialist.

Is HCM hereditary in children?

Yes, it follows an autosomal dominant pattern meaning every first-degree relative of a diagnosed child needs ECG and echo screening regardless of whether they have symptoms.

Can HCM cause sudden death in children during sports?

Yes and it’s one of the leading causes of sudden cardiac death in young athletes which is why every child with HCM needs a formal sport eligibility assessment before returning to competitive activity.

Does HCM get worse as a child grows?

It can because hypertrophy sometimes progresses during rapid adolescent growth which is why regular echo surveillance every one to two years is essential even in clinically stable children.

References:

How Does Kawasaki Disease Affect A Child’s Heart

How Does Kawasaki Disease Affect A Child’s Heart

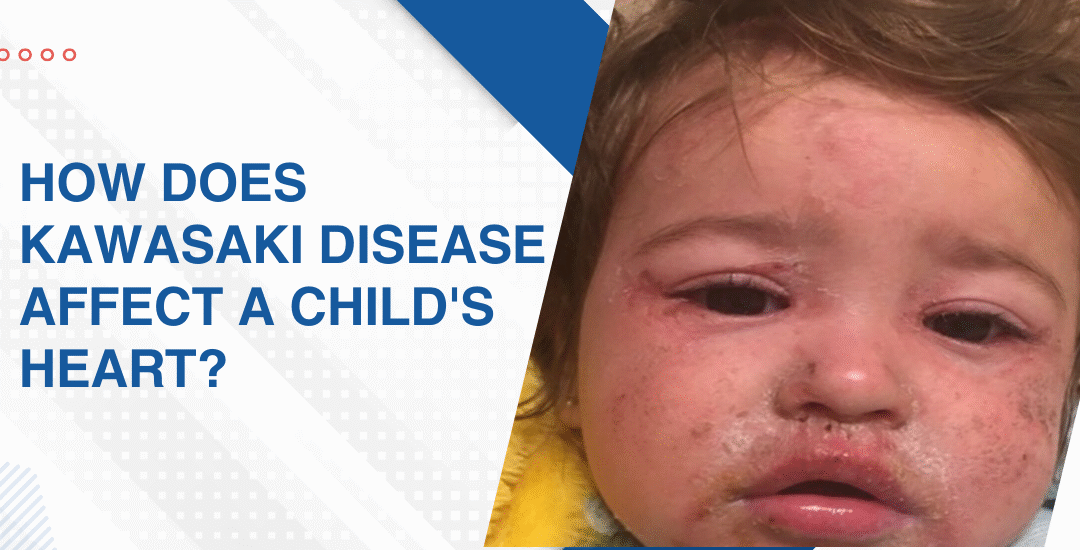
Kawasaki disease causes inflammation of blood vessels, primarily the coronary arteries that supply blood to the heart muscle itself. The most serious consequence is coronary artery aneurysms, weakened bulging vessel walls that can clot, narrow and trigger a heart attack in a child who should have had decades of normal cardiac life ahead. If it goes undetected or gets caught late, that damage doesn’t announce itself. It just builds.

“Most families I see have never heard of Kawasaki disease before the day their child was diagnosed and that gap between symptom onset and anyone thinking to check the coronary arteries is exactly where the damage quietly accumulates,“ says Dr. Prashant Bobhate, a Pediatric Cardiologist in Mumbai, India.

What Challenges Do Adults With Congenital Heart Defects Face?

It inflames the coronary arteries, weakens the vessel walls and in serious cases leaves behind aneurysms that don’t resolve and don’t forgive delays in detection.

  • Coronary aneurysms: Inflammation attacks the coronary artery walls directly and weakens them enough to bulge outward into structures that can clot, obstruct and eventually cause a myocardial infarction in a child whose peers are still in primary school.
  • Myocarditis: The heart muscle itself inflames during the acute illness alongside the vessels feeding it which explains why some children look far sicker than the fever alone would account for and why cardiac function needs active monitoring from day one not just at a follow-up echo weeks later.
  • Valve involvement: Mitral regurgitation develops in a small number of Kawasaki cases because inflammation affects the supporting structures of the valve alongside the coronary vessels and it’s worth looking for specifically on every acute phase echo rather than assuming valve integrity because the child appears clinically stable.
  • Electrical changes: Arrhythmias including prolonged QT interval occur during the acute inflammatory phase in some children and while these typically settle as inflammation resolves they’re another reason cardiac involvement needs evaluating from the start and not treated as an afterthought once the fever breaks.

Tracking exactly what the coronary arteries look like and how the heart muscle is functioning after Kawasaki is exactly what dedicated 2D echocardiography for children maps out properly before any long term management decision gets made.

How Is the Heart Watched After Kawasaki Disease?

This is where many children fall through the gap entirely.

  • Echo surveillance schedule: Frequency depends entirely on the coronary findings at diagnosis and a child with no coronary involvement confirmed at six weeks has a completely different surveillance need to one with a persistent medium aneurysm that’s still being tracked every few months.
  • Anticoagulation decisions: Children with large or giant coronary aneurysms need anticoagulation or antiplatelet therapy to reduce clot risk inside those weakened vessels and the choice between aspirin, warfarin and low molecular weight heparin depends on aneurysm size, age and the child’s overall clinical picture.
  • Stress testing as the child grows: A school-age child who had significant coronary involvement as a toddler needs periodic exercise stress testing as they get older because a narrowed coronary artery compensated at rest can reveal itself dramatically under physical load in ways a resting echo simply won’t catch.
  • Long term follow up into adulthood: Kawasaki is not a paediatric problem that ends at eighteen and adults who had giant aneurysms as children need specialist cardiac follow up that understands acquired coronary disease in a congenital context rather than a general cardiologist seeing an unusual presentation they weren’t trained to manage.

Parents wanting to understand what cardiac warning signs look like in children before any formal diagnosis gets made should read this piece on top 5 warning signs of pediatric heart failure because recognising when something is wrong early is always what changes what’s possible next.

Why Choose Dr. Prashant Bobhate for Kawasaki Heart Care in Mumbai?

You want someone who has read a Kawasaki echo on day five of the fever, tracked a medium coronary aneurysm across three years of follow-up appointments and had the honest conversation with parents about what a giant aneurysm means for their child’s cardiac future at forty. Not just what it means this week. Dr. Prashant Bobhate has spent over 12 years managing complex paediatric cardiac presentations including acquired coronary disease, myocarditis and the full range of inflammatory and congenital heart conditions across every age from newborn through adolescence at the Children’s Heart Centre, Kokilaben Dhirubhai Ambani Hospital.

Schedule a consultation to find out if a cure is possible and what the right treatment plan looks like for you.

FAQs

Can Kawasaki disease cause a heart attack in a child?

Yes and it’s the giant coronary aneurysms that carry the highest risk because a clot forming inside a weakened bulging artery in a five year old produces the same myocardial infarction physiology as it does in an adult with coronary disease.

How soon after Kawasaki disease should an echo be done?

Within the first week of diagnosis at minimum and then again at six to eight weeks because aneurysm formation can progress even after the fever resolves and the acute inflammation appears to have settled clinically

Does Kawasaki disease always affect the heart?

Not always but coronary artery abnormalities develop in around 25% of untreated children and even treated cases need echo surveillance because some coronary changes appear after the acute phase has apparently resolved.

Can a child fully recover from Kawasaki heart damage?

Small aneurysms often resolve within one to two years but giant aneurysms rarely regress completely and children carrying them into adulthood need lifelong cardiac surveillance regardless of how well they feel day to day.

References:

Call Now Button