Children’s Heart Surgery Under Ayushman Bharat

Children’s Heart Surgery Under Ayushman Bharat

Yes. Ayushman Bharat PM-JAY covers several congenital heart surgeries including VSD closure, ASD repair, TOF correction and PDA ligation under its cardiac surgery packages and eligible families pay nothing out of pocket at empanelled hospitals. Private health insurance also covers congenital heart surgery in most cases but waiting periods, sub-limits and what counts as a covered procedure vary significantly between policies and need to be verified before admission not after.

“Families who qualify for Ayushman Bharat often don’t know their child’s surgery is covered until someone tells them specifically and that gap between entitlement and awareness is something I try to close at the very first appointment because it changes everything about what’s actually accessible to them,” says Dr. Prashant Bobhate, Pediatric Cardiologist in Mumbai, India.

What Does Ayushman Bharat Cover for Children's Heart Surgery?

More than most families expect but with specific limits that matter enormously when the actual procedure is being planned and the hospital is being chosen.

  • Covered procedures: VSD repair, ASD closure, TOF correction, PDA ligation, pulmonary valvotomy and several other congenital cardiac surgeries fall within the PM-JAY package list and eligible children can access these at empanelled hospitals with zero out-of-pocket cost for the procedure itself.
  • Package limits: Each procedure has a fixed government package rate and when the actual cost of surgery at a private empanelled hospital exceeds that package ceiling the difference either gets absorbed by the hospital or falls on the family and understanding that gap before choosing a centre matters.
  • Empanelled hospitals only: Ayushman Bharat coverage only applies at hospitals officially empanelled under PM-JAY and not every cardiac centre in Mumbai that performs paediatric heart surgery is on that list so eligibility at a specific hospital needs to be confirmed before any admission happens.
  • Eligibility verification: The PM-JAY benefit is income and ration-card linked and families need to verify their eligibility through the official Ayushman Bharat portal or helpline before assuming coverage applies because assumptions at the hospital admission desk on surgery day create problems nobody needs at that moment.

Understanding what specialist paediatric cardiac care looks like at a dedicated centre and how to access it through available schemes is explored in this piece on the pediatric heart specialist at Kokilaben Hospital because knowing where the right care sits is the first step before the coverage question even becomes relevant.

What About Private Health Insurance for Children's Heart Surgery?

Complicated. Read the policy before the surgery not after.

  • Congenital condition clauses: Many older health insurance policies exclude congenital conditions entirely or impose a waiting period of two to four years before congenital heart surgery is covered and a family that discovers this on admission day faces a situation that proper policy review weeks earlier would have avoided.
  • Sum insured adequacy: A policy with a Rs 3 lakh sum insured covers a simple VSD closure at a government hospital but falls significantly short of a complex TOF repair at a private tertiary centre and families need to check whether their cover actually matches the procedure their child needs at the centre their cardiologist recommends.
  • Implant and device costs: Some insurers reimburse surgical fees but cap or exclude the cost of prosthetic valves, occluder devices and other implantable materials that form a significant portion of the total bill and those exclusions need to be identified in the policy document before the treatment plan is finalised.
  • Cashless vs reimbursement: Cashless admission requires the hospital to be on the insurer’s network and if the best centre for the child’s specific defect isn’t on that network the family may need to pay upfront and claim reimbursement later which requires financial capacity many families in this situation don’t have.

Parents wanting to understand what the cost picture looks like for open heart surgery in Mumbai across hospital tiers and what drives the final number should read this piece on top 5 warning signs of pediatric heart failure because catching a deteriorating defect before it becomes an emergency admission is always what keeps the most affordable and appropriate options available.

Why Choose Dr. Prashant Bobhate for Children's Heart Care in Mumbai?

A family navigating a congenital heart diagnosis while simultaneously trying to understand PM-JAY eligibility, insurance pre-authorisation and hospital empanelment needs a team that can help them work through all of it not just the clinical side. Dr. Prashant Bobhate has spent over 12 years working with families across every socioeconomic background at the Children’s Heart Centre, Kokilaben Dhirubhai Ambani Hospital and understands what it takes to make the right cardiac care accessible not just available in theory. Escorts Heart Institute New Delhi. Fellowship at University of Alberta Canada. Over 400 children on active cardiac therapies right now. He doesn’t send families away to figure out the system alone. He tells them exactly what their child needs and helps them find the clearest path to getting it.

📞 Call Now: (+91) 8080 826 898 A proper assessment tells you what procedure your child needs, whether Ayushman Bharat or your insurance covers it and what the realistic out-of-pocket picture looks like before any decision gets made.

Schedule a consultation to find out if a cure is possible and what the right treatment plan looks like for you.

FAQs

Which heart surgeries are covered under Ayushman Bharat for children?

VSD repair, ASD closure, TOF correction, PDA ligation and pulmonary valvotomy are among the covered procedures but the package list needs to be verified for the specific surgery the child requires at the empanelled centre.


Can a child get heart surgery free of cost in Mumbai under PM-JAY?

Yes at empanelled hospitals for covered procedures but the family must be eligible under PM-JAY income criteria, the hospital must be on the empanelled list and the procedure must fall within the approved package rates.


Does private health insurance cover congenital heart surgery in children?

Most major policies do but congenital condition waiting periods, sum insured limits and implant cost exclusions vary significantly between policies so the specific policy document needs to be checked before the admission is planned.


What if insurance doesn't fully cover the surgery cost?


The gap between insurance coverage and actual surgical cost can be bridged through hospital payment plans, charitable cardiac foundations or government welfare schemes and a specialist centre can usually guide families toward the right support option.


References:


 Children’s Open Heart Surgery Cost in Mumbai

 Children’s Open Heart Surgery Cost in Mumbai

In Mumbai’s private tertiary hospitals, children’s open heart surgery costs roughly between Rs 3 lakh and Rs 10 lakh depending on the defect, the complexity of the repair and the hospital tier. Simple VSD or ASD repairs sit at the lower end. Complex congenital corrections like TOF repair, arterial switch or Fontan procedures push significantly higher. The defect and the centre determine the number far more than any published price list does.

“Families call asking for a cost before they’ve even had an echo and I understand why. But giving a number before knowing the defect, the anatomy and what the repair actually involves would be like quoting a construction price before seeing the building,” says Dr. Prashant Bobhate, Pediatric Cardiologist in Mumbai, India.

What Factors Drive the Cost of Open Heart Surgery in Children?

Not one figure covers every child. The cost shifts significantly based on variables that are specific to each case and each centre and understanding them stops families from being blindsided when the actual estimate arrives.

  • Defect complexity: A straightforward VSD closure on bypass costs far less than a tetralogy of Fallot repair, a complete AVSD correction or an arterial switch operation for transposition and the surgical time, bypass duration and post-operative ICU requirement all scale with complexity.
  • ICU duration: This is usually the biggest variable families underestimate because a child who spends two days in cardiac ICU and one who spends ten days in the same unit after the same procedure can have final bills that differ by Rs 2 to 3 lakh from that single line item alone.
  • Hospital tier: A charitable or government-aided cardiac centre in Mumbai charges significantly less than a premium private hospital for an equivalent procedure and the gap can be Rs 2 to 4 lakh on the same surgery without necessarily reflecting a difference in surgical outcome for standard defects.
  • Implants and devices: Some repairs require prosthetic valves, conduits, pericardial patches or other implantable materials that are billed separately from the surgical fee and these costs vary by brand, size and whether Indian or imported equivalents are used.

Understanding what open heart surgery involves for a child’s specific defect and what the recovery looks like is exactly what a thorough pediatric heart failure management consultation maps out before any surgical planning begins.

What Else Goes Into the Final Bill?

More than most families expect upfront.

  • Pre-surgical workup: Echo, ECG, chest X-ray, blood work, cardiac catheterisation for pressure measurements and anaesthesia assessment all happen before the operation and these carry their own charges that rarely appear in the initial surgery quote families receive.
  • Anaesthesia fees: Paediatric cardiac anaesthesia is a subspecialty in itself and the anaesthesiologist’s fee in a private Mumbai hospital is billed separately from the surgical fee and can add Rs 30,000 to Rs 80,000 depending on procedure length and complexity.
  • Post-operative medications: Diuretics, anticoagulants, cardiac medications and antibiotics through the recovery period add up across the hospital stay and the first weeks at home and these ongoing medication costs continue well beyond the discharge date.
  • Follow-up echos and outpatient visits: Open heart surgery in a child doesn’t end at discharge because echo surveillance at one month, three months, six months and annually thereafter carries its own cost across years and this long tail of follow-up is something families need to budget for from the start not discover later.

Parents wanting to understand what the warning signs of an unrepaired cardiac defect look like before surgery becomes urgent should read this piece on top 5 warning signs of pediatric heart failure because recognising deterioration early is what keeps the surgical window open and the options on the table.

Why Choose Dr. Prashant Bobhate for Children's Heart Surgery Planning in Mumbai?

Surgical cost planning for a child’s heart condition needs someone who can tell a family exactly what procedure the anatomy requires, what that realistically costs at a centre that does it well and what the follow-up looks like across the years after the operation. Not a quote pulled from a brochure. A real conversation based on the actual echo in front of them. Dr. Prashant Bobhate has spent over 12 years working at the intersection of interventional cardiology and surgical co-management across congenital defects of every complexity at the Children’s Heart Centre, Kokilaben Dhirubhai Ambani Hospital. Escorts Heart Institute New Delhi. Fellowship at University of Alberta Canada. Over 400 children on active cardiac therapies right now. He tells families what the heart needs, what it costs and what happens next without dressing any of it up.

📞 Call Now: (+91) 8080 826 898 A proper assessment tells you exactly what surgery your child needs, what it realistically costs at a centre equipped to do it well and what the recovery and follow-up plan looks like from day one.

Schedule a consultation to find out if a cure is possible and what the right treatment plan looks like for you.

FAQs

What is the average cost of open heart surgery for a child in Mumbai?

Roughly Rs 3 lakh to Rs 10 lakh in private hospitals depending on the defect and complexity but simple repairs sit at the lower end and complex congenital corrections push well above that range.

Does health insurance cover children's open heart surgery in India?

Most major policies cover congenital heart surgery but pre-authorisation, waiting periods for congenital conditions and whether implant costs are included vary significantly between insurers so the policy needs to be checked specifically before admission.


Is open heart surgery in government hospitals in Mumbai cheaper?


Yes significantly and charitable cardiac centres offer the same procedures at a fraction of private hospital costs but waiting times and surgical volumes vary and families need to factor those alongside the cost difference.


What happens if open heart surgery in a child is delayed too long?


Progressive heart failure, rising pulmonary pressures and irreversible ventricular damage accumulate with delay and some defects that were straightforward corrections at six months become far more complex and risky operations at two years

References:


ASD Closure Surgery Cost In India 2026

ASD Closure Surgery Cost In India 2026

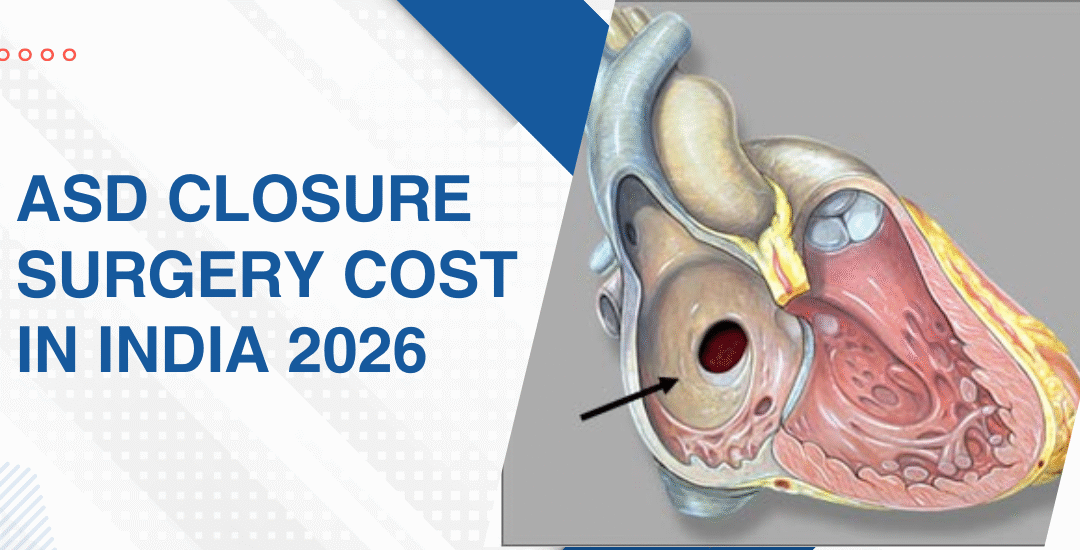
Device closure in India in 2026 costs roughly between Rs 1.5 lakh and Rs 3.5 lakh depending on the hospital, the device used and the city. Open heart surgical repair runs higher, typically between Rs 2.5 lakh and Rs 6 lakh or more at private tertiary centres. But the more important number isn’t the cost. It’s whether the anatomy supports device closure at all because that single question changes the entire cost picture.

“Families often come in having already looked up prices online and the number they find rarely matches what their child’s specific situation actually costs because the defect size, the device choice and whether surgery is even avoidable are all variables that a price list can’t account for” says Dr. Prashant Bobhate, Pediatric Cardiologist in Mumbai, India.

What Drives the Cost of ASD Closure in India?

Not one number fits every child. The cost of ASD closure depends on several variables that shift significantly from one case to the next and understanding them is what stops families from being surprised when the estimate arrives.

  • Device vs surgery: Catheter-based device closure is almost always cheaper than open heart surgery because it avoids the operating theatre, cardiopulmonary bypass, ICU admission and the extended hospital stay that surgical repair requires.
  • Device cost itself: The occluder device used in catheter closure is the single largest cost driver in a transcatheter procedure and the price varies depending on brand, size and whether a domestic or imported device is used for that specific defect anatomy.
  • Hospital tier: A government or trust hospital will quote significantly less than a premium private tertiary centre for the same procedure and the gap between the two can be substantial without necessarily reflecting a difference in surgical outcome for straightforward cases.
  • Defect complexity: A simple mid-septal secundum ASD with good rims costs less to close than a defect with multiple fenestrations, a deficient rim needing a larger device or an anatomy that requires intraoperative TOE guidance throughout a technically demanding catheterisation.

Every child being assessed for ASD closure deserves a detailed structural workup and atrial septal defect evaluation maps the anatomy properly before any cost estimate means anything at all.

What Else Should Families Budget For?

The procedure cost is only part of the picture.

  • Pre-procedure workup: Echo, ECG, chest X-ray, blood investigations and in some cases a cardiac MRI or catheterisation for pressure assessment all add to the total before the closure itself happens and families need to factor these in from the start.
  • Anaesthesia and OT charges: These are billed separately in most private hospitals and can add Rs 20,000 to Rs 60,000 on top of the procedure estimate depending on the complexity and duration of the catheterisation or surgical session.
  • ICU and ward stay: Device closure typically means one to two nights in hospital while surgical repair means a minimum of five to seven days and the daily room and ICU charges in a private tertiary centre accumulate faster than most families expect when they first see the procedure quote.
  • Follow-up echos: A device closure requires echo at one month, three months and six months post procedure to confirm device position and residual shunting and these follow-up visits carry their own charges that are rarely included in the initial procedure estimate families receive.

Parents wanting to understand what happens when an ASD goes unrepaired for too long and the pressure consequences that follow should read this piece on when lung transplant becomes necessary for pulmonary hypertension because the cost of delayed correction is always higher than the cost of timely intervention.

Why Choose Dr. Prashant Bobhate for Pediatric Cardiac Care in Mumbai?

Cost transparency matters but so does getting the right procedure recommendation in the first place because a family that pushes for device closure on an anatomy that needs surgery doesn’t save money they create a more complicated and expensive situation down the line. Dr. Prashant Bobhate has spent over 12 years performing catheter-based ASD closures and managing surgical referral pathways for defects where device closure isn’t the right answer at the Children’s Heart Centre, Kokilaben Dhirubhai Ambani Hospital.

Schedule a consultation to find out if a cure is possible and what the right treatment plan looks like for you.

FAQs

Is ASD device closure cheaper than open heart surgery in India?

Yes in most cases because it avoids bypass, ICU and a long hospital stay but the anatomy has to support a device and not every ASD qualifies regardless of what the cost difference looks like.

Does health insurance cover ASD closure surgery in India?

Most major health insurance policies cover ASD closure under congenital heart disease but the extent of coverage, pre-authorisation requirements and whether device cost is included varies significantly between insurers and policy types.

Can ASD closure be done at a government hospital in India?

Yes and the cost at government or trust hospitals is significantly lower than private centres but waiting times, device availability and surgical volumes vary and families need to weigh those factors alongside the price difference.


What happens if ASD closure is delayed due to cost?

An unrepaired ASD continues loading the right heart with excess blood volume and over years causes right heart enlargement, arrhythmia and eventually pulmonary hypertension that makes correction far more complex and expensive than it would have been done early.

References:

Pediatric Cardiologist Vs Pediatric Cardiac Surgeon

Pediatric Cardiologist Vs Pediatric Cardiac Surgeon

A pediatric cardiologist diagnoses heart conditions, manages them with medications and performs catheter-based procedures inside the heart without opening the chest. A pediatric cardiac surgeon operates. Opens the chest, works directly on the heart muscle, valves and vessels under cardiopulmonary bypass. Different training, different skills and in most cases a child needs both working together not one instead of the other.

“Families often arrive confused about who they’re seeing and why. The cardiologist is usually the one who finds the problem, decides what it needs and then brings the surgeon in when an operation is the answer. We work as a team not as alternatives to each other,” says Dr. Prashant Bobhate, Pediatric Cardiologist in Mumbai, India

What Does a Pediatric Cardiologist Actually Do?

The cardiologist is almost always the first specialist a child with a suspected heart problem sees and the one who stays involved across the longest stretch of that child’s cardiac life.

  • Diagnosis: Echo, ECG, Holter monitoring, exercise testing, cardiac catheterisation for pressure measurements and in some cases MRI interpretation all sit within the cardiologist’s domain before any surgical decision gets made.
  • Medical management: Medications for heart failure, pulmonary hypertension, arrhythmia and post-surgical recovery are all prescribed and adjusted by the cardiologist across months and years of follow up not handed off after one appointment.
  • Catheter procedures: Balloon valvuloplasty, ASD and VSD device closure, coil embolisation of a PDA and electrophysiology studies all happen in the catheterisation laboratory without a surgical incision and the outcomes in experienced hands are excellent for the right anatomy.
  • Long term surveillance: A child who had open heart surgery at three months still needs an echocardiogram at eight, fourteen and twenty-two and that longitudinal relationship across decades belongs to the cardiologist not the surgeon who operated once and stepped back.

If your child has been referred for assessment, understanding what interventional pediatric cardiology involves is a good place to start before the first appointment so the conversation makes sense when it happens.

When Does Open Heart Surgery Become the Only Answer?

A completely different disease. The valve is fine. The problem is deeper inside the lungs.

  • Vessel walls are the problem: In pulmonary hypertension the small arteries inside the lung tissue thicken, stiffen and narrow from the inside out and that progressive vascular resistance is what forces the right heart to push harder against a resistance it can never physically remove with a catheter balloon.
  • Multiple causes: PH can be idiopathic, secondary to congenital heart disease, autoimmune conditions, chronic lung disease or genetic mutations and identifying the underlying cause is what determines which drug pathway gets targeted first.
  • Treated with medications not procedures: Unlike stenosis there’s no valve to open or obstruction to cross because the resistance is distributed across millions of tiny vessels inside both lungs and management means targeted drug combinations working on specific molecular pathways simultaneously.
  • Progressive without treatment: Untreated pulmonary hypertension causes progressive right heart failure over months to years and the window for getting combination therapy started early before irreversible vascular remodelling sets in is something that genuinely cannot be recovered once it closes.

Families wanting to understand what the treatment journey for pulmonary hypertension actually looks like in real patients should read this piece on sotatercept changing how PAH is managed because the gap between what was possible two years ago and what’s achievable now for PH patients is significant and still widening.

Why Choose Dr. Prashant Bobhate for Pediatric Cardiac Care in Mumbai?

When a child has a heart condition the family needs a cardiologist who can do the diagnostic workup, perform the catheter procedure if the anatomy supports it and coordinate surgical planning when it doesn’t. All three in one place, not scattered across referrals that take weeks. Dr. Prashant Bobhate has spent over 12 years working at exactly that intersection of interventional cardiology and surgical co-management across congenital defects, pulmonary hypertension, arrhythmia and valve disease at the Children’s Heart Centre, Kokilaben Dhirubhai Ambani Hospital

Schedule a consultation to find out if a cure is possible and what the right treatment plan looks like for you.

FAQs

Does my child need a cardiologist or a cardiac surgeon first?

Almost always the cardiologist first because they diagnose the condition, decide what it needs and bring the surgeon in only when an operation is the right answer for that specific anatomy.

Can a pediatric cardiologist fix heart defects without surgery?

Yes for defects suitable for catheter closure like many ASDs, VSDs and PDAs but anatomy determines what’s possible and not every defect can be closed without opening the chest regardless of preference.

Do pediatric cardiologists and cardiac surgeons work together?

Always in a well-run centre because the cardiologist owns the diagnosis, the surveillance and the medical management while the surgeon owns the operative correction and both need to be aligned on timing and approach for the child to get the right outcome.


Will my child always need a cardiac surgeon?

Not always. Many congenital defects including moderate ASDs, small VSDs, pulmonary stenosis and PDA are managed entirely by the cardiologist through catheter-based procedures or medications without surgery ever becoming necessary.

References:

Pulmonary Stenosis vs Pulmonary Hypertension

Pulmonary Stenosis vs Pulmonary Hypertension

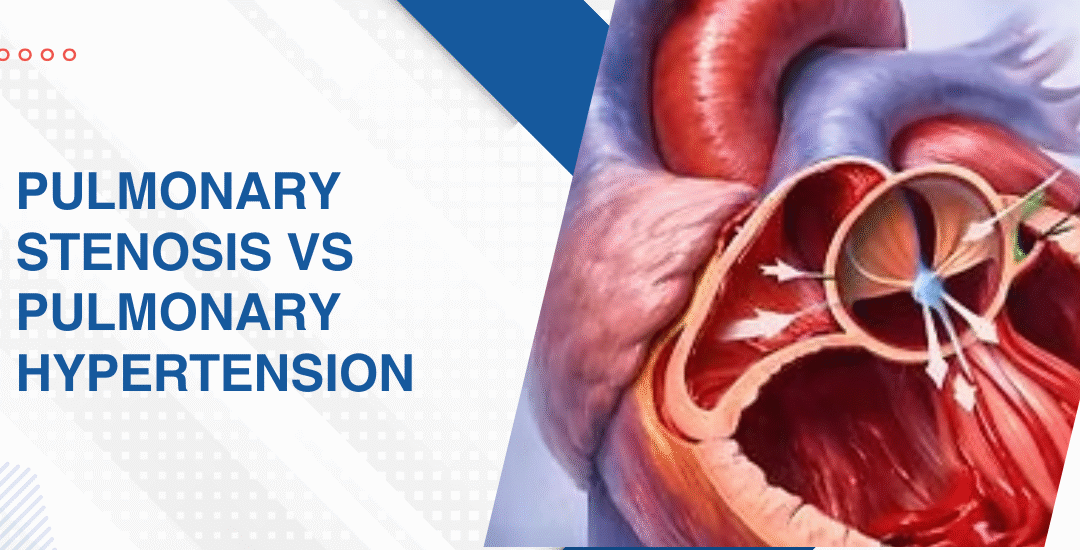
No, not even close. Pulmonary stenosis is a structural problem where the pulmonary valve is narrowed and obstructs blood from flowing out of the right ventricle. Pulmonary hypertension is a pressure problem where the blood vessels inside the lungs become abnormally resistant to flow. Same word at the front. Completely different diseases, different mechanisms and very different treatment paths.

“I explain it this way every time. Stenosis is a blocked gate. Hypertension is a flooded road. Both stress the right heart but for entirely different reasons and treating one like the other would be a serious mistake,” says Dr. Prashant Bobhate, Pediatric Cardiologist in Mumbai, India.

What Makes Device Closure the Right Choice for Some ASDs?

Pulmonary stenosis is a congenital structural defect. The valve leaflets are thickened, fused or malformed and that physical obstruction is what forces the right ventricle to generate higher pressure just to push blood through a narrowed opening it was never designed to fight against.

  • The valve is the problem: In pulmonary stenosis the obstruction sits at the valve itself and the right ventricle thickens over time trying to overcome that fixed mechanical resistance with every single beat.
  • Usually congenital: Most cases are present from birth, often picked up on fetal echo or early newborn screening, and mild stenosis can sit quietly for years while severe stenosis in a newborn needs intervention within days.
  • Balloon valvuloplasty fixes it: Moderate to severe pulmonary stenosis is treated by inflating a catheter balloon across the narrowed valve to split the fused leaflets open and the results in experienced hands are excellent without open heart surgery in most cases.
  • Pressure normalises after treatment: Once the obstruction is relieved the right ventricular pressure drops, the ventricle gradually de-thickens and most children go on to live entirely normal cardiac lives with periodic echo surveillance to confirm the valve stays adequate.

Understanding exactly what the pulmonary valve looks like and how much obstruction it’s generating is the first thing a proper pulmonary hypertension and structural evaluation maps out before anyone makes a management decision.

When Does Open Heart Surgery Become the Only Answer?

A completely different disease. The valve is fine. The problem is deeper inside the lungs.

  • Vessel walls are the problem: In pulmonary hypertension the small arteries inside the lung tissue thicken, stiffen and narrow from the inside out and that progressive vascular resistance is what forces the right heart to push harder against a resistance it can never physically remove with a catheter balloon.
  • Multiple causes: PH can be idiopathic, secondary to congenital heart disease, autoimmune conditions, chronic lung disease or genetic mutations and identifying the underlying cause is what determines which drug pathway gets targeted first.
  • Treated with medications not procedures: Unlike stenosis there’s no valve to open or obstruction to cross because the resistance is distributed across millions of tiny vessels inside both lungs and management means targeted drug combinations working on specific molecular pathways simultaneously.
  • Progressive without treatment: Untreated pulmonary hypertension causes progressive right heart failure over months to years and the window for getting combination therapy started early before irreversible vascular remodelling sets in is something that genuinely cannot be recovered once it closes.

Families wanting to understand what the treatment journey for pulmonary hypertension actually looks like in real patients should read this piece on sotatercept changing how PAH is managed because the gap between what was possible two years ago and what’s achievable now for PH patients is significant and still widening.

Why Choose Dr. Prashant Bobhate for Pulmonary Valve and PH Care in Mumbai?

You need someone who can look at a right ventricular pressure of 80mmHg on echo and tell you immediately whether that’s coming from a stenotic valve that a balloon can fix in one sitting or from pulmonary vascular disease that needs a three-drug combination and a decade of follow up. Those are not the same conversation and they don’t belong with the same cardiologist. Dr. Prashant Bobhate has spent over 12 years managing both structural right heart disease including pulmonary stenosis and balloon valvuloplasty and complex pulmonary hypertension across every cause and every age group at the Children’s Heart Centre, Kokilaben Dhirubhai Ambani Hospital.

Schedule a consultation to find out if a cure is possible and what the right treatment plan looks like for you.

FAQs

Can a child have both pulmonary stenosis and pulmonary hypertension?

Yes and it happens in some congenital heart conditions where a structural defect has also driven up pulmonary pressures over time and distinguishing the contribution of each requires detailed catheterisation not just an echo.

Is pulmonary stenosis serious in children?

Mild stenosis often needs only monitoring but moderate to severe stenosis needs balloon valvuloplasty before the right ventricle sustains the kind of pressure overload damage that doesn’t fully reverse even after the obstruction is relieved.

Can pulmonary hypertension be mistaken for pulmonary stenosis?

It can on a basic assessment because both cause right heart pressure elevation but an echocardiogram in experienced hands distinguishes them clearly and the treatment implications of getting that distinction wrong are significant.


Does pulmonary stenosis cause pulmonary hypertension?

Not directly but longstanding unrepaired stenosis causes right heart dysfunction that can indirectly affect pulmonary circulation and some congenital defects that include pulmonary stenosis also carry independent pulmonary hypertension risk.

References:

Call Now Button